Validation and Prospective Testing of a High Sensitivity, Quantitative Analytic Assay for HER2 on Histopathology Slides
medRxiv. 2025. DOI 10.1101/2025.05.06.25327097. PMID 40385428. PMCID PMC12083604.
How to cite
AMA
Chan NNN, Gaule P, Benanto J, Scott L, Robbins CJ, He M, et al. Validation and Prospective Testing of a High Sensitivity, Quantitative Analytic Assay for HER2 on Histopathology Slides. medRxiv. 2025. doi:10.1101/2025.05.06.25327097APA
Chan, N. N. N., Gaule, P., Benanto, J., Scott, L., Robbins, C. J., He, M., et al. (2025). Validation and Prospective Testing of a High Sensitivity, Quantitative Analytic Assay for HER2 on Histopathology Slides. medRxiv. https://doi.org/10.1101/2025.05.06.25327097BibTeX
@article{chan2025validation,
  title   = {Validation and Prospective Testing of a High Sensitivity, Quantitative Analytic Assay for HER2 on Histopathology Slides},
  author  = {Chan, N. N. N. and Gaule, P. and Benanto, J. and Scott, L. and Robbins, C. J. and He, M. and others},
  journal = {medRxiv},
  year    = {2025},
  doi     = {10.1101/2025.05.06.25327097},
  pmid    = {40385428}
}
HER2-targeting antibody-drug conjugates now benefit patients whose tumors carry only low levels of HER2. But the companion test that decides who receives them, a pathologist reading a stained slide by eye, was built to flag high, gene-amplified HER2, and it separates the low range poorly and subjectively.
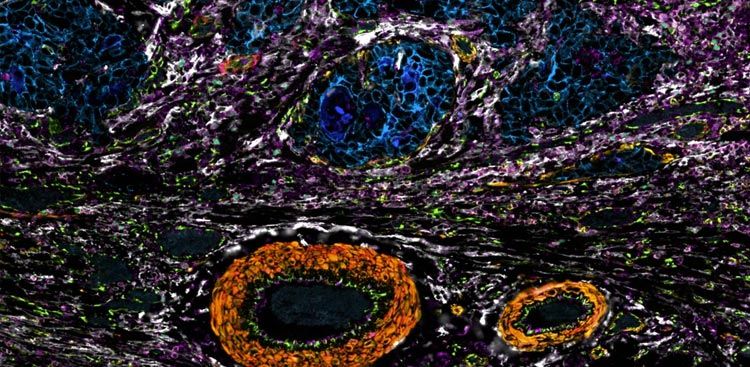
This team built a fully quantitative immunofluorescence assay that reports HER2 as an absolute protein concentration, in attomoles per square millimetre, then validated its precision and ran it on 316 prospective breast cancer core biopsies. Many tumors a pathologist had scored as having little or no HER2 in fact carried measurable amounts above the assay’s reporting threshold — the kind of objective readout that could help flag patients for HER2-targeted therapy that a by-eye score can miss.
Key findings
- The quantitative assay measured HER2 with high precision. On a 40-case breast cancer validation set, the inter-assay coefficient of variation was 10%, with intra-assay and inter-operator precision of 6.4% and 7.3% respectively.
- Pathologist scores disagreed with quantitative HER2 in the low range. Across 316 prospective core biopsies, 71% of cases scored IHC 0 and 84% of cases scored IHC 1 measured above the assay’s limit of quantification, while only 6% of the whole cohort fell below its limit of detection.
- HER2 was reported on an absolute, continuous scale. The assay quantified HER2 protein in attomoles per square millimetre, with a lower limit of quantification of 1093 amol/mm2 and a reportable range extending to the highest prospective case at 9434 amol/mm2.
CyteFinder in the methods
“All QIF slides of control CMAs and breast cancer cases stained by the HS-HER2 assay were scanned at 20X magnification on the CyteFinder HT II multiplexed fluorescent imaging platform (RareCyte, Seattle WA). The CyteFinder imaging platform uses advanced, high speed, multi-channel systems with integrated machine learning algorithms, designed for digital pathology and clinical laboratories. We used the optimized fixed exposure times and specific filter sets for individual fluorophores i.e., DAPI for nuclear compartment, Alexa Fluor 546 for tumor CK masking and Cy5 for HER2 target.”
— Chan et al., medRxiv (2025), Methods, “Digital Fluorescent Imaging and Image Processing”
Why it matters for CyteFinder users
If you are weighing CyteFinder for quantitative tissue imaging, look at the role it played here. Turning a fluorescent slide into an absolute HER2 concentration only works if the raw signal is captured the same way on every slide, in every batch, on every day; otherwise the number drifts and the calibration curve means nothing. That is the job the instrument did. Every calibrator microarray and all 316 prospective biopsies were scanned at a fixed magnification, with fixed exposure times and set filter sets for each fluorophore, so intensities stayed directly comparable across the whole study. That reproducible multi-channel capture is what let the team anchor readings to cell-line standard curves and report HER2 in attomoles per square millimetre, with inter-assay variation of 10%. For your own workflow, the point is that quantitation is won or lost at the imaging step: if acquisition is not standardized, no downstream analysis can recover an absolute, comparable number.